Assisted Reproduction
CONTENTS
Book an appointment
Discuss your case with the physician and find out what the next steps are.
Infertility is defined as the inability of a couple to achieve conception and have a child after at least one year of regular sexual intercourse without contraceptive protection.
The evaluation of a couple experiencing a fertility problem requires a systematic assessment due to the variety of conditions that may lead to infertility.
FERTILITY ASSESSMENT – WOMAN
- FSH increases with age, as well as in women with few oocytes in the ovaries
- LH may be elevated in Polycystic Ovary Syndrome
- Estradiol
- Prolactin: may be elevated in menstrual cycle disorders
- Progesterone : for ovulation assessment on day 21 of a 28-day cycle
- Thyroid function testing and anti-thyroid antibodies
- AMH (Anti-Müllerian Hormone) :It is an indicator of the number of oocytes in the ovaries and predicts the ovarian response to stimulation with hormones in cases of assisted reproduction

Ovulation assessment plays a central role in the evaluation of women, as it is associated with almost one third of all infertility problems. Some women experience certain symptoms with ovulation (mild abdominal pain lasting a few hours or brownish vaginal discharge). However, the majority of women do not have such symptoms. Alternatively, a woman may use an ovulation kit that tests certain hormones in the urine or record daily changes in body temperature and cervical mucus. However, because these methods are not considered very accurate, the physician can confirm ovulation with ultrasound monitoring performed 2–3 times during the cycle. In addition, in order to confirm ovulation and determine the proper function of the corpus luteum, progesterone testing is recommended on the specific day of the cycle indicated by the physician.

The uterine environment plays a very important role in the process of fertilization, and its thorough assessment is necessary before drawing conclusions about the possible causes of infertility. Possible problems that may be encountered during this assessment include:
- Congenital uterine anomalies (e.g. uterine septum, bicornuate uterus)
- Acquired uterine abnormalities (e.g. endometrial adhesions)
- Polyps, fibroids, adenomyosis
All of the above may be associated with difficulties in achieving pregnancy or with miscarriages. For their diagnosis, we use one or more of the following examinations:
Gynecological ultrasound: transvaginal gynecological ultrasound of the internal genital organs provides direct and painless imaging of the uterus. In recent years, we have been using a more sensitive form of ultrasound, 3D (three-dimensional) gynecological ultrasound, which allows us to diagnose congenital uterine anomalies with great accuracy and has practically replaced magnetic resonance imaging for this purpose.
Hysteroscopy: this is a simple examination during which a camera is inserted into the uterine cavity through the cervix, while the woman is under sedation. With the use of an appropriate light source, we are able to view the inside of the uterus on a monitor.
Hydrosonography: this is a newer imaging method that combines conventional gynecological ultrasound (or even three-dimensional ultrasound) with the use of water (more precisely, normal saline) inside the uterus. During this examination, the saline helps us clearly visualize the inside of the uterus and diagnose whether or not a polyp is present. In this way, we can avoid a potentially unnecessary hysteroscopy.
ASSESSMENT OF FALLOPIAN TUBE PATENCY

Good function of the fallopian tubes is an essential prerequisite for achieving pregnancy. The patency of the fallopian tubes is assessed using the following methods:
Hysterosalpingography: the older method, which has been used for decades. It must be performed in a radiology laboratory. It consists of injecting contrast fluid through the cervix and imaging the uterine cavity as well as the fallopian tubes with X-rays.
Hysterosalpingo-contrast sonography (HyCoSy): this is the newer method for assessing the fallopian tubes and combines effectiveness with simplicity and safety. It consists of injecting a special contrast agent into the uterine cavity and the fallopian tubes and using ultrasound to diagnose tubal patency. In other words, it works in the same way as conventional hysterosalpingography, but without the problem of ovarian radiation exposure. It is also much less painful than conventional hysterosalpingography and takes place in the familiar environment of a gynecological clinic rather than in a radiology laboratory. In addition, with this method we can perform a complete examination of the uterus and ovaries in real time.

- Gonorrhea
- Vaginal Haemophilus
- HIV
- Hepatitis B
- Hepatitis C
- Cytomegalovirus
- Rubella
- Toxoplasma

FERTILITY ASSESSMENT – MAN
The male factor accounts for 40% of the cause of the problem in subfertile couples.
Evaluation of the male factor is performed with a semen analysis. If this is abnormal, it may need to be repeated after 1 month. It is important to obtain a complete medical history, including questions regarding the husband’s diseases, surgeries or injuries, medication use, history of sexually transmitted diseases, occupation, and smoking. Assessment by a specialized urologist may also be required.
In cases of an abnormal semen analysis, the solution may be in vitro fertilization, either with the conventional IVF method, or with intracytoplasmic sperm injection – ICSI, or with testicular biopsy. With these techniques, many couples with fertility problems due to a male factor have had their own children.
Instructions for semen collection
Semen collection should be carried out according to the following instructions:
- There must be abstinence from sexual intercourse or ejaculation for a period of 2 days. This period is calculated without counting the day of intercourse and the day of the examination.
- Collection is usually performed at the laboratory.
- Semen collection may also be performed at home, provided that transport does not take more than one hour. During transport, keep the sample at a temperature of 18–30 °C, away from sunlight.
- If collection is performed at home, inform the laboratory of the exact time of collection.
- Before collection, wash the genitals and hands thoroughly with soap and rinse with plenty of water. Wear clean underwear.
- Collection is performed in a sterile container, which you can obtain from a pharmacy.
- Collection must be performed by masturbation and without the use of a condom.
- Try to collect all the material in the sterile container so that the examination is reliable. If this is not possible, inform the laboratory.
Semen analysis – Normal values
- Volume: 2.0 ml or greater
- pH: 7.2-8.0
- Sperm count: 15,000,000/ml or greater
- Total sperm count: at least 40,000,000 per ejaculation
- Motility: 40% with overall excellent and moderate movement
- Morphology: at least 3% normal forms
- Leukocyte count: Less than 1,000,000/ml
DNA fragmentation is a break in one or both strands of the DNA of the sperm chromosome. When this occurs, there may be unexplained inability to conceive (with a normal semen analysis) or recurrent miscarriages.
Normal DNA fragmentation values are up to 25%. Factors responsible for increased DNA fragmentation include infections, smoking, exposure to environmental pollutants, advanced age, varicocele, recent episodes of high fever, and conditions that predispose to increased testicular temperature (e.g. laptop between the legs).
To improve DNA fragmentation values, a diet rich in fruits and vegetables is recommended, as well as the intake of antioxidant dietary supplements, vitamins C and E, coenzyme Q10, carnitine, selenium, zinc, folic acid, smoking cessation, and treatment of infections. Testing for sperm DNA fragmentation is performed exactly like a semen analysis (with simple semen production by the man).
SPERM CYTOGENETIC TESTING (FISH TECHNIQUE)
International literature reports that subfertile men with a normal peripheral blood karyotype have a higher frequency of chromosomal abnormalities in spermatozoa compared with men with normal semen parameters. Indicatively, the most common chromosomal abnormalities are an abnormal number of sex chromosomes or a structural chromosomal abnormality (e.g. translocation of genetic material from one chromosome to another). Consequently, an increased number of embryos with chromosomal abnormalities may be created, resulting in reduced chances of success of the in vitro fertilization attempt.
The criteria for sperm cytogenetic testing and sperm apoptosis include:
Repeated biochemical/missed pregnancies in women under 35 years of age, with a normal peripheral blood karyotype
Poor-quality embryos in women under 35 years of age, with a normal peripheral blood karyotype
Inability of sperm to fertilize
Men who have undergone radiotherapy or chemotherapy
Men with oligo-astheno-teratozoospermia
Unexplained infertility

TREATMENTS

Monitoring of the menstrual cycle is the simplest form of assisted reproduction. The assistance provided involves monitoring follicular development, identifying the timing of ovulation, and scheduling sexual intercourse. We do not stimulate the ovaries with medication, and therefore it is the most natural method of assisted reproduction.
Procedure: Normally, every woman produces and releases one egg each month. If she has a 28-30 day cycle, ovulation (i.e. the release of the egg from the ovary) occurs between the 12th and 16th day of the cycle. In the menstrual cycle monitoring method, an ultrasound is performed on the 10th day of the cycle (day 1 is the first day of the period). This ultrasound will show us the size of the dominant follicle and the thickness and nature of the endometrium.
When the diameter of the follicle reaches 16 millimeters, the woman is advised to start using ovulation tests (daily), which she can obtain from the pharmacy. When the ovulation test is positive, the couple is advised to begin having sexual intercourse for the next three days, starting on the day of the positive ovulation test.
Which women are indicated for this type of treatment?
- Women who have a normal menstrual cycle (28-30 days) and ovulate every month
- Women with unexplained infertility of short duration (less than 6 months)
- Women without other hormonal or anatomical problems
Advantages
- It is the simplest form of assisted reproduction
- The woman does not take any medication
- There is no possibility of multiple pregnancy (since we do not stimulate the follicles)
- The cost of treatment is very low
Disadvantages
- The pregnancy rate is rather low (less than 10%)
- The couple must be patient, as it may take longer to achieve conception with this method.
This is a procedure for enhancing ovulation, with the aim of increasing the number of oocytes released per cycle and maximizing the chances of conception. In cases of an irregular menstrual cycle or known anovulation, we use preparations to induce ovulation, such as clomiphene citrate and, alternatively, letrozole (FEMARA).
Indications
Women with anovulation (regular transvaginal ultrasound examination)
Mild ovarian stimulation in women with a low response to conventional stimulation (poor responders)
Age under 35 years
In cases where conventional ovarian stimulation is not permitted for medical reasons
In women with a history of breast cancer (Letrozole/Femara)
Monitoring of the procedure is carried out by performing regular transvaginal ultrasound examinations and blood hormone testing in order to assess the effect of administering hormonal preparations and to individualize the dosage according to the examination findings.
Clomiphene Citrate: Clomiphene citrate is the substance that binds to estrogen receptors in the brain, resulting in a false message being sent to the brain that there is a lack of estrogen. This message stimulates the brain to produce, through the pituitary gland, larger amounts of endogenous gonadotropins (FSH, LH) than those produced in a natural cycle, which in turn stimulate the ovaries to produce more than one follicle.
It is usually administered from the 3rd to the 7th day of the cycle at a dosage of 100 mg per day, with the dose increased to 150 mg if the ovarian response is not satisfactory. Follicles are considered mature when their size is greater than 18 mm in mean diameter, at which point the hormone human chorionic gonadotropin hCG is administered in order to induce the final maturation of the follicles, which, 32-36 hours later, will lead to spontaneous ovulation. If pregnancy is not achieved after 4-6 treatment cycles, then more potent preparations, such as gonadotropins, are used.
The advantages of the treatment are its low cost and ease of administration, while the disadvantages include the low pregnancy rate of 8-15% per cycle, the possibility of twin or ectopic pregnancy, the possibility of ovarian hyperstimulation, drug failure, and all side effects such as vasomotor symptoms and alteration of the fluidity of cervical mucus.
Letrozole (FEMARA): This is a substance that selectively inhibits the aromatase enzyme and drastically reduces estrogen production by the tissues. Its main indication is its adjunctive administration in cases of women who have undergone surgery for breast cancer, in order to be protected from the hormones produced by the body.
Their property of inhibiting estrogen production is also used in infertility for ovulation induction. Low estrogen levels force the pituitary gland to produce larger amounts of endogenous gonadotropins (FSH, LH) than those produced in a natural cycle, which in turn stimulate the ovaries to produce more than one follicle.
It is usually administered from the 3rd to the 7th day of the cycle at a dosage of 4 mg per day, with the dose increased to 6 mg if the ovarian response is not satisfactory. Follicles are considered mature when their size is greater than 18 mm in mean diameter, at which point the hormone human chorionic gonadotropin hCG is administered in order to induce the final maturation of the follicles, which, 32-36 hours later, will lead to spontaneous ovulation.
The advantages of the treatment are its low cost, ease of administration, and safety of use in women with breast cancer. The disadvantages include the low pregnancy rate of 8-15% per cycle, the possibility of twin or ectopic pregnancy, the possibility of ovarian hyperstimulation, drug failure, and other side effects, mainly headache and general fatigue.
Unlike clomiphene citrate, letrozole does not cause alteration of cervical mucus; therefore, its use does not necessarily need to be accompanied by intrauterine insemination.
Intrauterine insemination (IUI) is the direct injection of spermatozoa into the inner cavity of the uterus (endometrium) and aims to increase the number of spermatozoa introduced into the fallopian tubes; consequently, fertilization of the oocytes is assisted. Regardless of whether a semen sample is produced fresh or thawed, it must be processed to separate the viable (motile) spermatozoa from the other components of the seminal fluid. If the seminal fluid is not properly processed and is placed in the uterus as it is, substances known as prostaglandins may cause uterine contraction, which expels the injection, while at the same time there is an increased risk of infection.
The insemination procedure is relatively straightforward and does not cause pain or significant discomfort to the patient. The specialist physician first inserts the speculum so as to identify the best access to the cervical os. After vaginal lavage is performed, a thin and flexible catheter is inserted through the cervix into the uterus. Its exact position is clarified using abdominal ultrasound. The spermatozoa are slowly deposited in the center of the uterine cavity, while the ultrasound confirms the successful injection.
An obvious disadvantage of insemination when it is performed after hormonal stimulation of the ovaries is the possibility of multiple pregnancies and the associated risks that may follow, such as ovarian hyperstimulation, preterm birth, and increased miscarriage rates.
Success rates vary depending on age, the couple’s fertility problem, and whether the treatment includes ovarian stimulation (increased number of oocytes) or is performed during a natural cycle (one oocyte only). On average, the success rate with the intrauterine insemination method is 20% for each new attempt.
IN VITRO FERTILIZATION (IVF) IN A NATURAL CYCLE
 The first successful in vitro fertilization attempt in Manchester in 1978 was performed using the natural cycle method. Although in the years that followed the use of medications for ovarian stimulation significantly changed the landscape, in recent years the natural cycle method has been used increasingly as an alternative to the use of medications.
A natural cycle is the method in which we do not administer medications to stimulate the ovaries and retrieve multiple oocytes, as is done in conventional IVF. Instead, we monitor the follicle that the woman produces naturally on her own during the cycle.
Monitoring is performed with transvaginal ultrasound, as well as with measurement of hormones in the blood. When the follicle has grown sufficiently, to approximately 16–17 millimeters, an injection of gonadotropin is then administered for its final maturation (Pregnyl, Ovitrelle), and, after 36–38 hours, oocyte retrieval is performed. Once the oocyte has been collected and fertilized, the resulting embryo is placed in the uterus using the standard embryo transfer method, 2–3 days after oocyte retrieval.
The advantage of the natural cycle is that we do not administer medications for ovarian stimulation. Although IVF medications have been used for 25 years and do not appear to be implicated in adverse health effects, many women are hesitant to take injectable hormones. With the natural cycle method, the stimulation stage is bypassed, and the only medications used are non-injectable medications after oocyte retrieval, intended to improve the likelihood of embryo implantation in the uterus and the achievement of pregnancy.
In addition, the main complications of conventional IVF are avoided: Ovarian Hyperstimulation Syndrome and Multiple Pregnancy.
This method is used in women who either cannot take medications for various medical reasons or have a poor response to them (poor responders). It may also be used in women who have had multiple failed attempts with poor-quality embryos.
The disadvantage of the natural cycle is that the success rates of the method are clearly lower compared with conventional IVF using medications. The probability of finding an oocyte during oocyte retrieval, fertilizing it, and developing a good-quality embryo in the laboratory is approximately 50–60%. Once embryo transfer of a good-quality embryo has been performed, the probability of pregnancy may approach 35%, always depending on the woman’s age.
In summary, the natural cycle method can be used with fairly good success rates either in women who do not wish to take medications for ovarian stimulation or in women whose response to medications is poor.
IN VITRO FERTILIZATION (IVF) WITH STIMULATION (USE OF MEDICATIONS)
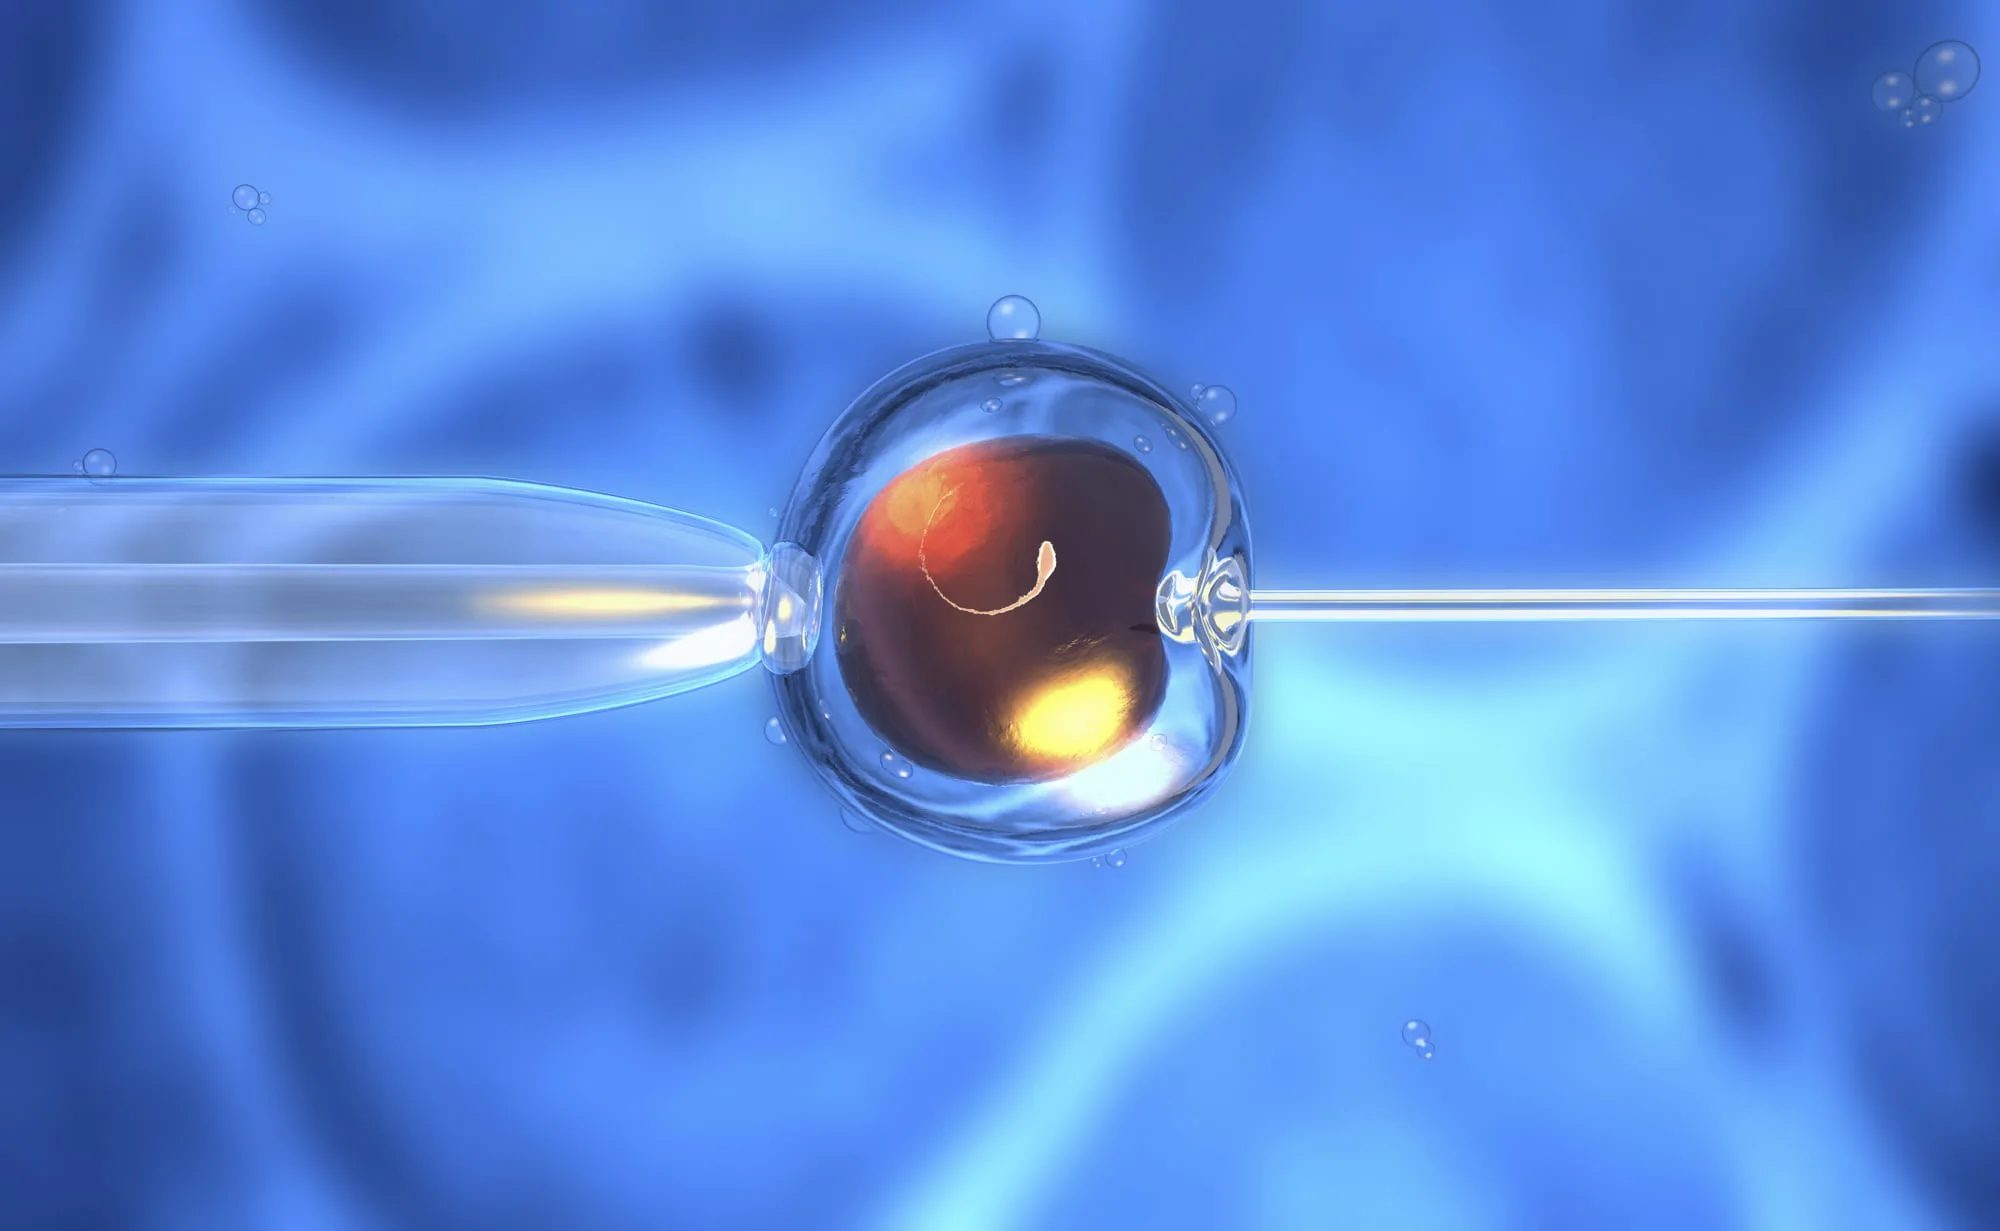
For many couples with fertility problems, in vitro fertilization (IVF) is the best solution for achieving pregnancy. It can be applied to address a variety of causes of infertility, such as mild sperm problems, endometriosis, tubal damage, or unexplained infertility. During the process of conventional in vitro fertilization, the oocytes are fertilized by spermatozoa in the laboratory environment (rather than in the woman’s fallopian tubes). Fertilization can be achieved either through the process of conventional in vitro fertilization (IVF) or by the method of microfertilization (intra-cytoplasmic sperm injection – ICSI).
The history of IVF
Robert G. Edwards was destined to become the most famous biologist of his time when, on July 25, 1978, he announced the birth of Louise Brown, the first “test-tube baby,” in England, together with obstetric surgeon Patrick Steptoe and midwife Jane Purdie. Since then, developments have been rapid: a revolution was marked when successful microfertilization with intracytoplasmic sperm injection (ICSI) was announced in 1992 (Palermo), along with its variants, MESA (Silber & Asch, 1992) and TESE (Schoyssman, 1993). The male factor in infertility is considered to have been practically eliminated. In Greece, the first child conceived by in vitro fertilization was born on January 20, 1982, and was the 13th test-tube baby worldwide.
The stages of in vitro fertilization – Procedure
The treatment cycle with in vitro fertilization includes the following stages:
Investigation and diagnosis of infertility
Preliminary tests
Ovarian stimulation with medication (12–14 days), with the aim of developing multiple follicles. We select the type of protocol based on the specific characteristics of each woman’s cycle, age, previous attempts, and other factors that we assess.
Monitoring with a series of ultrasound scans and hormonal measurements. Monitoring is performed every two to three days in order to optimize the daily dosage of medications and with the aim of achieving the best outcome for your attempt.
Induction of final oocyte maturation (single evening injection). On the day when the follicles have matured sufficiently, the final injection is administered, which will schedule the final maturation of the oocytes and ovulation.
Oocyte retrieval (collection of the oocytes). Retrieval of the oocytes from the ovaries is performed transvaginally by puncture and continuous ultrasound guidance. Oocyte retrieval is brief in duration (10–30 minutes) and practically painless because it is performed under sedation.
Sperm collection (collection of semen). In cases of azoospermia, testicular biopsy (TESE) is recommended.
Fertilization of the oocytes by spermatozoa. At this laboratory stage, the oocytes come into contact with the spermatozoa. When the semen has normal parameters, conventional IVF is selected as the fertilization method. In the conventional method, no intervention is performed. For many couples with poor sperm quality, where the spermatozoon is unable to fertilize the oocyte on its own, microfertilization (ICSI – Intracytoplasmic Sperm Injection) is selected as the treatment method, allowing successful fertilization of the oocytes even in difficult cases of severe oligoasthenoteratozoospermia. The following day, the embryologist checks and records the percentage of normally fertilized oocytes.
Embryo culture After fertilization, the embryos are cultured in the laboratory for 2–6 days, up to the blastocyst stage. Proper division of their cells is a key criterion for their quality.
Embryo transfer Selection of the best embryos and their transfer into the uterine cavity. Two to six days after oocyte retrieval, the embryos are transferred to the uterus. It is a painless procedure that does not require sedation. With the help of a thin catheter, the embryos are transferred into the intrauterine cavity.
Pregnancy testing (13 days after embryo transfer, with a blood test to determine the level of the hormone beta-human chorionic gonadotropin)
Clinical pregnancy assessment with transvaginal ultrasound (4 weeks after embryo transfer).
Assessment of ongoing pregnancy at the 12th week of gestation, i.e. 10 weeks after embryo transfer.
Optional procedures (depending on medical history)
Embryo or oocyte cryopreservation. Cryopreservation allows the preservation of oocytes, spermatozoa and embryos for an extended period of time (five years or more). With the application of the new cryopreservation method, vitrification, it appears that survival and pregnancy success rates are higher compared with slow controlled freezing
Assisted hatching, this is a technique performed in the laboratory that facilitates hatching of the embryo. It is recommended when the zona pellucida of the embryos is thick or hard, in cryopreserved embryos, and in women with previous failed attempts
Preimplantation genetic diagnosis (PGD) for the detection of genetic abnormalities and Preimplantation Genetic Screening (PGS) using the new array CGH method, in cases of patients for whom it is considered necessary.
ENDOMETRIAL PREPARATION AND BLASTOCYST TRANSFER
For many years, couples undergoing in vitro fertilization treatment have had the option of freezing and cryopreserving surplus embryos that are not transferred to the uterus at the end of treatment. The embryos are stored in liquid nitrogen and can be used at a later date.
Embryo cryopreservation is performed using the new vitrification method, after the embryos have reached the blastocyst stage (day 5 or 6), in order to ensure that only embryos with good developmental potential are stored. When it is decided to use them, these embryos are thawed and, at the appropriate stage of the woman’s cycle, transferred to the endometrium.
SPERM RETRIEVAL BY TESTICULAR OR EPIDIDYMAL BIOPSY
Surgical sperm retrieval (TESE)
Surgical sperm retrieval is recommended in cases of azoospermia, inability to ejaculate, or failure of induced ejaculation with electrostimulation. The procedure is performed under intravenous or local analgesia. The testicular tissue obtained undergoes special processing by the embryologist in order to identify spermatozoa. After motile spermatozoa have been isolated, fertilization of the oocytes follows using the intracytoplasmic sperm injection method. Any surplus spermatozoa may be cryopreserved for future use. There are various methods of surgical sperm retrieval, either from the epididymis or from the testes.
Retrieval of spermatozoa from the epididymis
- Microsurgical epididymal sperm aspiration – MESA: Recommended in cases of obstructive azoospermia with normal spermatogenesis. It involves surgical opening of the epididymis using a microscope and aspiration of epididymal fluid to identify spermatozoa.
- Percutaneous epididymal sperm aspiration – PESA: Recommended in cases of obstructive azoospermia with normal spermatogenesis. It is performed by puncturing the epididymis using a 19–21G needle.
Retrieval of spermatozoa from the testis
- Fine needle aspiration – FNA: Recommended in cases of obstructive azoospermia with normal spermatogenesis. It is performed by puncturing the testis using a fine 21G needle.
- Testicular sperm aspiration-TESA: Recommended in cases of obstructive azoospermia with normal spermatogenesis.
- Testicular sperm extraction – TESE: Recommended in cases of obstructive and non-obstructive azoospermia and involves open biopsy and collection of small fragments of testicular tissue.
Methods of sperm aspiration from the epididymis (MESA, PESA) or the testes (TESA) are simpler; however, they are largely “blind” procedures, causing damage to testicular tissue, such as hematoma, fibrosis and testicular atrophy. Testicular biopsy (TESE) is recommended in the international literature as the most effective method for identifying spermatozoa and is associated with a lower complication rate.
CRYOPRESERVATION – STORAGE OF SPERM AND TESTICULAR TISSUE

Historical background
The first reference to the possibility of freezing sperm was made in 1776 by Spallanzani after successful experiments he conducted involving the freezing and thawing of human sperm in snow. In essence, however, the first sperm freezing took place in 1949, when Polge and his colleagues observed the cryoprotective effect of the substance glycerol on avian sperm frozen at -76 degrees Celsius. This was followed in 1953 by Sherman and Bunge, who were the first to freeze human sperm in a 10% glycerol and dry ice solution. The first pregnancy from spermatozoa that had been frozen in a glycerol solution and liquid nitrogen was achieved by the same research team a few years later. In the 1970s, the first human sperm cryopreservation banks were established, while the birth in 1979 of the first child conceived through in vitro fertilization, Louise Brown, gave new impetus to the improvement of sperm freezing techniques.
How is sperm cryopreservation – freezing performed?
Sperm can be frozen through an appropriate procedure and stored in containers containing nitrogen at -196 degrees Celsius. The most widely used method involves adding an appropriate volume of cryoprotective material, such as glycerol at a concentration of 5–10%, to the sperm, followed by freezing of the sample with or without the use of a controlled-rate freezing device. Although no major changes in outcomes have been observed, in recent years more complex solutions have also been used to improve the cryopreservation method, containing substances other than glycerol, such as egg yolk, soy lecithin, amino acids and citrate. Frozen sperm can be stored without losing its properties and fertilizing capacity for many years, even decades.
Indications – advantages of sperm freezing – cryopreservation.
- In men who are about to undergo chemotherapy or radiation due to cancer, which is expected to significantly affect their fertility. In men who are about to undergo orchiectomy or prostatectomy due to a benign or malignant tumor, in order to preserve their fertility in the future.
- In men who are about to undergo sterilization (vasectomy – ligation of the spermatic ducts) so that their fertility may be reversible.
- In men with poor quality of life, such as heavy smoking, high and daily alcohol consumption, daily exposure to occupational risk factors (chemical substances, radiation, excessive heat), who wish, through sperm cryopreservation, to preserve their fertility in the distant future.
- Couples undergoing IVF cycles where the husband’s physical presence will not be possible on the day of oocyte retrieval (long-distance business trips, unforeseen events at work), etc.
- In men who have erectile dysfunction and cannot ejaculate or have a complete absence of spermatozoa in the ejaculate, spermatozoa can be collected directly from the epididymis and the testis, and the collected spermatozoa can be frozen for future use, safeguarding the patient’s fertility.
- In men who have suffered an accident (spinal cord injury) and often cannot ejaculate, the quantity and quality of sperm decreases over time. In these cases, storing and preserving sperm as early as possible can largely protect their fertility.
- In men who wish to have children at a later time and want to secure their reproductive potential, as a precautionary measure.
- In men who have successfully undergone treatment to improve sperm quality but have a low probability of maintaining this result, they can use cryopreservation to freeze their sperm, which at this point in time is satisfactory in quantity and quality.
- In men with severe oligoasthenospermia when concentration of the ejaculate material from multiple collections is required.
The possibility was provided to create sperm banks and to use sperm donation at any point in time, for couples facing a serious problem of azoospermia.
Since the beginning of its application in 1978, in vitro fertilization has been the most important scientific discovery for the treatment of infertility. Developments since then have raised the effectiveness of the method to very high levels. An important role in this direction was played by the development of a new, innovative method of embryo cryopreservation, vitrification. The vitrification method allows the safe preservation of embryos, achieving survival rates exceeding 98% after thawing!
The high effectiveness of the new cryopreservation method has enabled specialists to adopt new, more effective practices in the application of in vitro fertilization.
One such emerging and important practice, which in recent years has been gaining increasing ground internationally, is planned embryo cryopreservation and transfer in a subsequent cycle.
In certain cases during an in vitro fertilization cycle, it may be found that the endometrium does not have the ideal conditions for implantation. Factors that may affect endometrial function and therefore the implantation process may include the medication itself used during in vitro fertilization, ovarian hyperstimulation syndrome, as well as pathological findings that may be identified during treatment, such as an endometrial polyp, a very thin endometrium, etc. Today, thanks to the vitrification method, it is possible to cryopreserve all embryos for as long as necessary, until ideal conditions in the endometrium are ensured before the embryo transfer of the precious embryos. Planned embryo cryopreservation and embryo transfer in a subsequent cycle is a new, modern approach that allows us to transfer embryos only when endometrial conditions are ideal, thereby maximizing the chance of pregnancy.
The preservation of surplus embryos resulting from an in vitro fertilization cycle has been a known and recognized method for many years. However, thanks to the vitrification method, the effectiveness of embryo preservation has been maximized! Almost 100% of embryos survive after thawing and remain just as capable of leading to pregnancy as fresh embryos. This new advanced capability allows the couple to complete their family without the need for repeated treatment procedures and puts into practice the plan: “one stimulation treatment – one family”!
Experience to date has shown that the results from the implantation of embryos that have been cryopreserved using the vitrification method are just as good as the results we have from the transfer of fresh embryos, and in some cases even better, due to the ideal endometrial conditions that we ensure! Both the cryopreservation of surplus embryos and planned embryo cryopreservation and embryo transfer in a subsequent cycle are powerful tools for individualized treatment for each couple.
OOCYTE CRYOPRESERVATION – FERTILITY PRESERVATION

Unfertilized oocyte cryopreservation is a method that has recently begun to be applied in the field of Assisted Reproduction and is used in cases such as:
- Women with premature ovarian insufficiency
- Women who are about to undergo oncological treatment and have an increased risk of loss of fertilizing capacity
- Women who wish to preserve their fertility and postpone starting a family
- Couples who, for ethical or religious reasons, wish to avoid embryo freezing
The first report of pregnancy from frozen oocytes was achieved by Chen in 1986. Since then, few children have been born worldwide, because the process of freezing unfertilized oocytes using the slow-freezing method did not have high success rates. The main cause was the difficulty of cryopreserving cells with a high water content, such as oocytes.
In contrast, the recently used vitrification method, according to the international literature, appears to be successfully applicable for the cryopreservation of unfertilized oocytes. The survival rate of oocytes after thawing exceeds 90%, the fertilization rate is approximately 70%, while the pregnancy rate is greater than 40%. For the collection of oocytes for cryopreservation, the woman undergoes hormonal ovarian stimulation, as in the case of In Vitro Fertilization. The procedure lasts approximately 9–12 days, during which she undergoes ultrasound monitoring and blood sampling for analysis at regular intervals. Once the oocytes have matured sufficiently, they are removed with a fine needle inserted through the vagina under ultrasound guidance. The procedure is not painful, lasts a short time, and the woman is under sedation, a form of light anesthesia. The collected oocytes are immediately frozen at -196 degrees Celsius and remain stored until the woman decides that it is the right time to become a mother”
Unfertilized oocyte cryopreservation is a very promising method that reflects the modern living conditions of Greek women and appears able to offer much in the field of assisted reproduction

In vitro fertilization using donor eggs concerns women who:
- Are experiencing premature menopause
- Have a history of repeated failed IVF attempts
- Have a history of recurrent miscarriages
- Have a history of poor egg quality
- Have a history of hereditary disease
It is a scientifically documented procedure with excellent results; in specialized units, success rates are above 50%.
At the Unit with which we collaborate, this technique has been applied for more than 15 years with excellent results and within a framework of responsibility and the application of particularly strict scientific and ethical criteria.
Based on Greek legislation in force since 2005, donors are healthy Greek women under 35 years of age who, in the context of their own treatment and voluntary donation or egg sharing, anonymously consent to donating a specific number of eggs.
Donors provide a detailed personal and family history and are screened for
- infectious diseases (hepatitis, AIDS, syphilis, etc.),
- hematological diseases (thalassemia, cystic fibrosis),
- the presence of chromosomal abnormalities by karyotype.
The external characteristics of the two women are also matched.
The egg recipient must be assessed to ensure the good condition of her uterus, and appropriate hormonal preparation of the uterus must be carried out for embryo reception. The waiting time for finding eggs is between 5 and 6 months.
Surrogacy is used by women who, for medical reasons, have undergone removal of the uterus—while having retained their ovaries—or whose uterus does not function properly, or when another reason arises that prevents them from carrying a pregnancy. In these cases, another woman is used, in whose uterus the embryo or embryos resulting from the fertilized egg of the other woman with her partner’s sperm are placed. The two women play the central role in this process: the biological mother and the surrogate mother, or otherwise the “birth mother”, who carries the embryo of the first woman and subsequently gives birth to the child.
There are various genetic or acquired diseases and disorders that may make pregnancy impossible and lead to the choice of surrogacy. Typical examples include:
● Hysterectomy (surgical removal of the uterus for medical reasons)
● Mayer-Rokitansky-Küster-Hauser (MRKH) syndrome
● Previous injuries and scarring of the uterus
● The presence of multiple fibroids in the uterus
● Certain medical conditions that make pregnancy risky (heart disease, kidney diseases, etc.4)
● Cases of multiple miscarriages
● Multiple failures in in vitro fertilization attempts
● Dangerous complications in a previous pregnancy
● Asherman syndrome (multiple intrauterine adhesions)
Legislation and surrogacy
Under the current law concerning assisted reproduction in our country, the process of a third woman carrying a couple’s embryo is permitted only by court decision. The application must be submitted exclusively by the woman who wishes to have a child and is unable, for medical reasons, to carry the pregnancy, while a prerequisite is that she must not have exceeded the age of 50. In addition, specific documents—medical opinions—are required, clearly proving the relevant inability to carry a pregnancy.
Similar requirements that apply to the surrogate mother are that her age must range from 25 to 45 years, that she must have had at least one child of her own, and that she must not have undergone more than two caesarean sections. Furthermore, in order to confirm her suitability, diagnostic tests and a psychological evaluation are carried out. A common requirement for both women is that they reside in Greece. It is of vital importance to emphasize that any financial compensation is expressly prohibited.
In summary, the legislation in our country is very specific; however, in general terms it is quite favorable. Legal guidance should always be in place in order to avoid any complications during the process. A private agreement must also be drawn up between the couple, the center, and the surrogate mother, in order to protect all parties.
Choosing surrogacy is something that can truly change your life. There is a great deal of information and the procedures are detailed, but every step is worthwhile. We are here to do it with you!

GENETICS
PREIMPLANTATION GENETIC DIAGNOSIS (PREIMPLANTATION GENETIC DIAGNOSIS, PGD)

Preimplantation genetic diagnosis (PGD)
Preimplantation genetic diagnosis (PGD) is a laboratory procedure performed before embryo transfer in order to identify hereditary genetic diseases in the embryo. In this way, we are able to detect gene mutations associated with specific conditions before the stage of embryo transfer and implantation, resulting in the prevention of diseases before the onset of pregnancy and, by extension, the birth of healthy children. Specific gene mutations are sought (using the PCR method) that are responsible for the occurrence in the embryo of known congenital and hereditary diseases. The technique can be applied at the stage of either the unfertilized mature oocyte (first polar body biopsy), the day-3 embryo (blastomere biopsy), or the blastocyst (trophectoderm biopsy).
Patients for whom PGD is indicated are:
- Couples who are carriers of a monogenic or sex-linked disease.
- Couples who wish to have an HLA-compatible baby who will serve as a bone marrow donor for another affected child in the family.
Examples of diseases for which preimplantation genetic diagnosis is applied include beta-thalassemia, cystic fibrosis, etc. With the continuous progress of genetics, the identification of more genes responsible for specific hereditary diseases is expected, making it possible to avoid more diseases, even forms of cancer.
Preimplantation genetic diagnosis has advantages over the usual methods of prenatal testing, namely amniocentesis and chorionic villus sampling, because the possibility of terminating the pregnancy is avoided if the test gives positive results for the specific condition of the embryo. Finally, it must be made clear that the method looks for specific diseases and does not rule out the birth of a child with another type of genetic defect.
PREIMPLANTATION GENETIC SCREENING (PREIMPLANTATION GENETIC SCREENING, PGS)

PGS (Preimplantation Genetic Screening)
The aim of PGS is to identify structural or numerical chromosomal abnormalities (aneuploidies), including chromosomal deletion, addition, or translocation, in embryos of couples known to be euploid. Forty to sixty percent of preimplantation embryos are aneuploid, which is a possible etiology for the relatively low implantation efficiency in both natural conception and in vitro fertilization. The main indications for the use of PGS in IVF treatments include advanced maternal age, recurrent implantation failure, and recurrent miscarriages. The success of PGS depends largely on technical expertise, embryo quality, and the presence of mosaicism in preimplantation embryos. Isolated cells are tested for structural or numerical abnormalities of a series of chromosomes using cytogenetic methods (fluorescence in situ hybridization, FISH). Today, biopsy of day-three embryos is the most common method. However, blastocyst biopsy is rapidly becoming the preferred method due to the reduced likelihood of mosaicism and the increased amount of DNA available for diagnosis.
Patients for whom PGS is indicated are:
- Couples in which the women are of advanced age. More than half of embryos derived from women aged 35–40 years present chromosomal abnormalities. This percentage increases significantly as the woman’s age increases.
- Couples with a history of recurrent miscarriages and/or failed IVF attempts.
The benefits of PGS are:
- Higher chance of pregnancy
- Reduced risk of miscarriage
- Greater confidence in transferring a single embryo, avoiding the risks associated with twin or multiple pregnancy
- Reduced number of IVF cycles required to achieve pregnancy
- There is currently considerable debate as to whether PGS is ultimately a technique that can help and increase pregnancy rates. This is due to the mosaicism observed in embryos, which may lead to an incorrect diagnosis. For this reason, studies are underway to determine whether preimplantation genetic screening can become established in the field of assisted reproduction and substantially help infertile couples.
With regard to PGS technology, two newer methods that offer significantly increased diagnostic accuracy are comparative genomic hybridization (CGH) and next-generation DNA sequencing (New Generation Sequencing, NGS).
BOOK AN APPOINTMENT

He supports scientific excellence in clinical practice and recognizes the possibilities offered by modern reproductive methods to couples who wish to have their own child.
His profileThis information is for general guidance only and does not replace a medical examination and advice.
