Dr. Alexandros Traianos on the ultrasound machine screen

FETAL MEDICINE

Prenatal screening

Prenatal screening aims at the timely diagnosis and treatment of pathological conditions that could affect the normal course of pregnancy and the health of the mother and fetus.

Diploma Holder in Fetal MedicineFetal Medicine Diploma

PRENATAL SCREENING

Invasive andnon-invasive methods.

Dr. Alexandros Traianos, a Fetal Medicine Diploma holder, provides all invasive and non-invasive methods covering the full spectrum of prenatal screening.

ULTRASOUND EXAMINATIONS

Ultrasound Examinations

First-trimester nuchal translucency scan

First trimester

Nuchal translucency

  • When it is performed11 weeks and 1 day to 13 weeks and 6 days
  • CRL45mm – 84mm

This ultrasound scan is performed from 11 weeks and 1 day to 13 weeks and 6 days (CRL 45 mm–84 mm). It is usually performed transabdominally, but in some cases it may be necessary to carry out the examination transvaginally.

The test in detail

Objectives of the ultrasound examination

Accurate dating of the pregnancy
This is particularly important for women who cannot remember the date of their last menstrual period, have irregular menstruation, or conceived while breastfeeding or immediately after stopping the contraceptive pill. We measure the size of the fetus and, based on this, calculate the estimated due date (40 weeks).
Assessment of the risk of Down syndrome and other chromosomal abnormalities
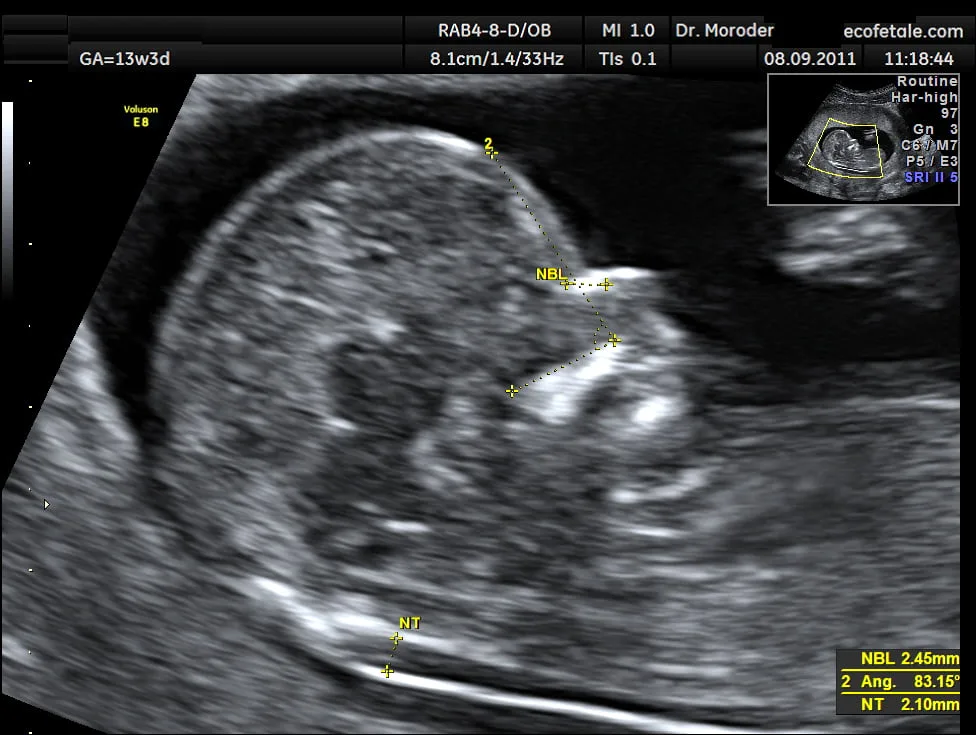
Every woman should receive an assessment of her individual risk for this pregnancy. This is calculated by taking into account the mother’s age, the measurement of two hormones in her blood (PAPP-A and free beta-human chorionic gonadotropin), and four ultrasound markers: nuchal translucency (the fluid behind the fetus’s neck), which is the most important marker; the nasal bone; blood flow on the right side of the fetal heart (at the tricuspid valve); and blood flow in the fetal ductus venosus (a small vessel in its liver). Parents will receive comprehensive counseling regarding the significance of this risk and the various options for further testing.
Diagnosis of multiple pregnancy
Approximately 2% of natural conceptions and 10% of IVF conceptions result in a multiple pregnancy. Ultrasound can determine whether both fetuses are developing normally and whether the babies share the same placenta, which may lead to problems during pregnancy. In such cases, it would be advisable for the pregnancy to be monitored more closely.
Diagnosis of certain major congenital anomalies
Significant abnormalities may be visible at this gestational age, but the 20-week ultrasound scan is also necessary.
Diagnosis of early pregnancy failure (missed miscarriage)
Unfortunately, in 2% of women who attend for the nuchal translucency ultrasound scan, it is found that the fetus has died, often several weeks earlier and without any warning. Couples will receive comprehensive counselling regarding the possible causes of this problem and the options for the next steps that may be necessary.
Risk assessment for pre-eclampsia and fetal growth restriction
In all patients, at the end of the examination, blood flow in the mother’s uterine arteries will be measured ultrasonographically using Doppler assessment. The result of this examination can indicate which women are at increased risk of developing pre-eclampsia, mainly before 34 weeks, as well as which fetuses are at risk of developing growth restriction, primarily in the third trimester.
Risk assessment for preterm birth
In all patients, at the end of the examination, if they so wish, the length of the cervix will be measured transvaginally. We know that during pregnancy the cervix should be long and closed. In women who are found to have a short cervix during the examination, the risk of preterm birth is increased. Management in this case depends on the nature of the problem.
Individualized risk for Down syndrome

The vast majority of babies are normal. However, all women, regardless of their age, have a small risk of giving birth to a child with a physical and/or intellectual disability. In some cases, the abnormality is due to a chromosomal abnormality, such as Down syndrome.

The only way to know with certainty whether the fetus has a chromosomal abnormality is through a diagnostic invasive test, such as chorionic villus sampling (CVS) or amniocentesis. However, these tests carry a risk of miscarriage of approximately 1%.

It is up to you and your partner to decide whether the risk of the fetus having chromosomal abnormalities is high enough to justify invasive testing. As a guideline, an invasive test is usually offered if the risk of Down syndrome is 1 in 300 or higher.

The most accurate method for assessing the risk that the fetus has Down syndrome is performed between the 11th and 14th weeks of pregnancy and depends on the following:

  • Maternal age
  • Amount of fluid behind the fetal neck (nuchal translucency)
  • Presence or absence of the fetal nasal bone
  • Fetal heart rate
  • The blood flow through the tricuspid valve of the fetal heart
  • The blood flow through the ductus venosus in the fetal liver
  • Presence or absence of any structural abnormalities
  • Levels of the two hormones (free β-hCG and PAPP-A) in the mother’s blood

After the ultrasound examination, based on all the above factors, the estimated risk for Down syndrome will be discussed with you. Only you can decide whether you wish to undergo an invasive diagnostic test. Regardless of whether or not you have decided to have an invasive test, a detailed ultrasound examination at 20 weeks is recommended to check for structural abnormalities in the fetus.
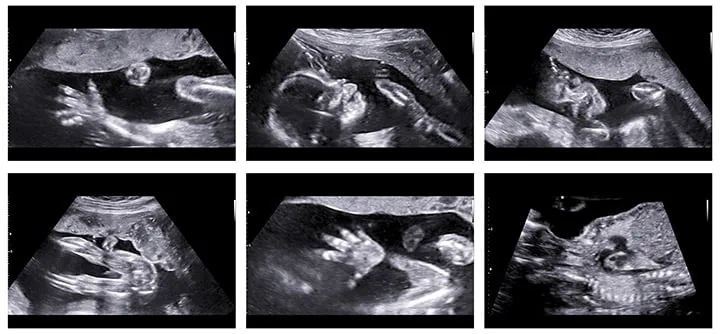

Fetal images from a level II (anomaly) scan

Second trimester

Second-level ultrasound scan

  • When it is performed20–22 weeks of gestation

This is a detailed ultrasound examination at 20–22 weeks of gestation.

The test in detail

During the ultrasound examination, we assess in detail the anatomy and all systems of the fetus, determine the position of the placenta, evaluate the amount of amniotic fluid, and assess fetal growth by calculating the fetal weight. Particular attention is given to the brain, face, spine, heart, stomach, bowel, kidneys, and limbs. Determination of the sex is possible with the couple’s consent.

In women at high risk of preterm birth (multiple pregnancies, history of preterm birth, abnormalities of the uterus or cervix, previous surgery), we can also perform a transvaginal ultrasound to measure the length of the cervix.

If any abnormalities are detected, the significance of the findings will be discussed and the parents will have the opportunity to receive further counselling. Additional testing, including the Harmony test, or invasive procedures, such as amniocentesis, can also be explained in depth.

What are the indications or reasons for this ultrasound examination?The ultrasound examination is recommended for all expectant mothers.

Third-trimester growth scan with Doppler

3rd trimester

Growth ultrasound (Doppler)

  • When it is performedFrom the 28th week until delivery, usually at the 32nd week
  • Examination duration~ 30 minutes

This is an examination recommended for all pregnancies.

The test in detail

The purpose of this examination is:

  • the detection of a possible problem in fetal development.
  • confirmation of the good condition of the fetus.
  • the examination of the baby’s third-trimester anatomy.
  • the assessment of the risk of preterm birth.
  • the assessment of the risk of pre-eclampsia and fetal growth restriction.

It is performed from the 28th week up to delivery, but usually in the 32nd week of pregnancy.

The growth ultrasound (Doppler) includes a series of fetal measurements (biometry) that allow us to calculate the fetal weight. The measurement values are entered into the Astraia software, which, with its extensive database, can reliably indicate whether the baby is developing in line with other babies of the same gestational age.

Blood flow (using color Doppler) is examined in the vessels of the umbilical cord in order to assess placental sufficiency, and in the cerebral vessels in order to assess oxygenation of the child’s brain.

The amount of amniotic fluid is measured and fetal movements are assessed, providing information about the well-being of the fetus. In addition, the position and morphology of the placenta are evaluated.

The fetus is a developing organism, and various pathological conditions may have an adverse impact on the development of its vital organs. For this reason, during the growth ultrasound, the fetal anatomy in the third trimester is also assessed. Specifically, the skull and brain, the lenses of the eyes, the palate, the lips and facial profile, the spine, the neck, the thorax and lungs, the heart, the abdominal wall, the gastrointestinal system, and the fetal kidneys are examined for the detection of possible pathology.

The third-trimester anatomy examination is performed by obtaining specific ultrasound planes, as defined by the corresponding protocols of the Fetal Medicine Foundation (FMF), which have been shown to have the highest sensitivity in detecting possible abnormalities at this advanced gestational age.

In cases where the fetus is in an appropriate position, imaging is performed using three-dimensional (3D and 4D) ultrasound.

The growth ultrasound (Doppler) can be combined with cardiotocography (biophysical profile). This combination provides us with additional information about the condition of the fetus and the risk of intrauterine death.

PROCEDURES

Procedures

Ultrasound-guided chorionic villus sampling

Chorionic villus sampling

Chorionic Villus Sampling – CVS

  • When it is performed11–15 weeks

This is essentially a placental biopsy involving the sampling of chorionic villi, i.e. its structural components. The fetus and the placenta originate from the same dividing cell, the fertilized egg, and therefore the chromosomes found in the placental cells are the same as those of the baby.

The test in detail
When is it performed?

This is an examination performed at 11–15 weeks.

How is chorionic villus sampling performed?

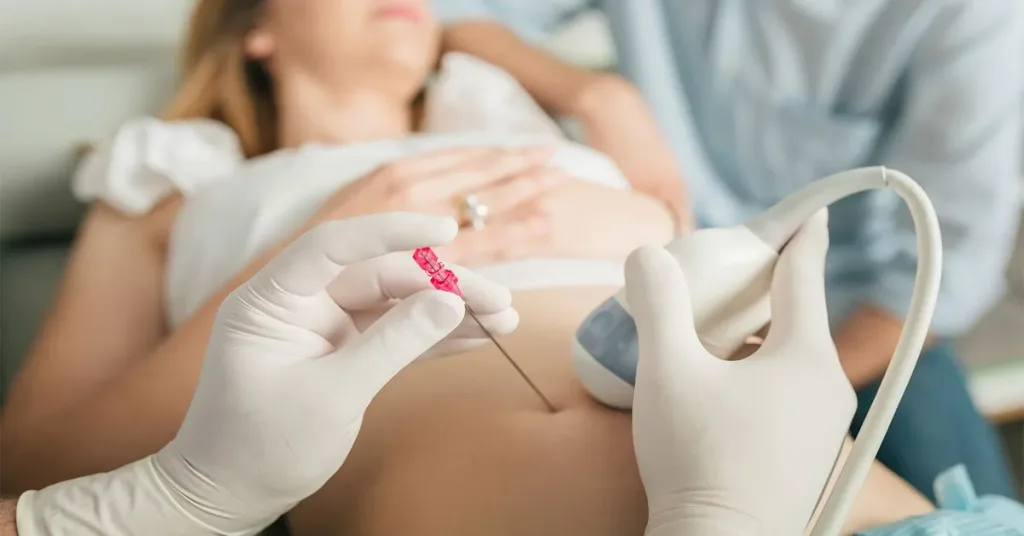
Careful antisepsis of the abdominal area is performed. The entry site is selected with care and a local anesthetic (xylocaine) is administered. A fine needle is then passed through the mother’s abdomen into the uterus and placenta, and a sample of chorionic villi is obtained by aspiration. The position of the needle is continuously monitored by ultrasound. The procedure takes a few minutes. The needle does not enter the amniotic cavity and does not disturb the fetus. After the examination is completed, the fetal heartbeat is checked.

What can I expect after chorionic villus sampling?

During the first 2–3 days, you may experience some mild abdominal discomfort, similar to period pain, or slight vaginal bleeding. These are relatively common symptoms and, in the vast majority of cases, the pregnancy continues without problems. You may take simple painkillers, such as paracetamol (Depon). If you experience severe pain, have heavy bleeding, or develop a high temperature, seek medical advice.

Is bed rest necessary?

We usually advise bed rest for 1 day and limiting strenuous physical activities for 2–3 days.

We must not overlook the prophylactic administration of anti-D gamma globulin in Rh-negative women.

When can I expect the results?

The initial results (PCR - 99%) for Down syndrome and other common chromosomal abnormalities are usually available the next day or the day after. The subsequent results (molecular karyotype) for rarer chromosomal abnormalities are available within 1 week. The final result is available in 2 weeks, after completion of the cell line culture.

Can the procedure need to be repeated?

In approximately 1 in 1,000 cases, the invasive procedure will need to be repeated because the results are unclear, usually due to mosaicism, i.e. the condition in which the placenta contains both normal and abnormal cells, sometimes in a significant proportion. The abnormal cells may not involve fetal tissues, as nature has isolated them in the placenta only, at an early stage. In this rare case, it is necessary to perform amniocentesis at a later time, which does not carry the risk of mosaicism.

What are the risks associated with chorionic villus sampling?

The risk of miscarriage due to chorionic villus sampling is approximately 1 in 300 and is the same as the risk of amniocentesis after 18 weeks. The risk decreases as the days pass and disappears after the first five days.

Ultrasound-guided amniocentesis

Diagnostic invasive examination

Amniocentesis

  • When it is performedAfter the 15th week, ideally 16th–20th
  • DurationOne minute

This is a diagnostic invasive examination involving the analysis of cells, DNA, and metabolites in the fluid surrounding the baby (amniotic fluid). The cells in the amniotic fluid originate mainly from the fetus, and therefore the chromosomes of these cells are the same as those of the fetus.

The test in detail
How is amniocentesis performed?

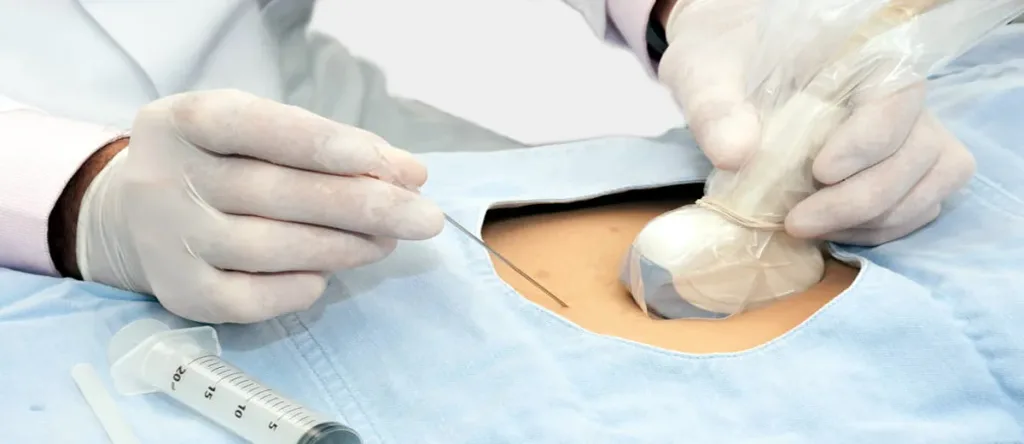
Under ultrasound guidance, a very fine needle (finer than the one used for chorionic villus sampling) is passed through the skin of the mother’s abdomen, and 15–20 ml of amniotic fluid is taken from the amniotic sac around the fetus and sent to the laboratory.

The amniotic fluid collected consists of fetal urine; therefore, the amount taken for testing is replenished within just a few hours.

The procedure takes one minute, and we listen to the baby’s heartbeat immediately afterward.

Is amniocentesis painful?

According to women’s testimonies, amniocentesis is not painful. However, mild discomfort in the form of pressure is to be expected. Local anaesthetic is not used, as the amniocentesis needle is thinner than the needle used for local anaesthesia, and the procedure lasts one minute.

When and why is amniocentesis performed?

Amniocentesis is performed after the 15th week of pregnancy and up to the end of pregnancy. However, it is ideally recommended during the period between the 16th and 20th weeks of pregnancy, while for chromosomal testing the 32nd week of pregnancy is recommended as the upper limit, because due to increased dilution of the amniotic fluid, after this stage of pregnancy it becomes more likely that no result will be obtained from the laboratory.

Indications

The examination is performed following specific indications, such as:

  • Abnormal nuchal translucency examination.
  • Abnormal alpha/triple test result.
  • Suspicious ultrasound findings.
  • Previous pregnancy with a fetus affected by a chromosomal abnormality.
  • Perinatal infection (toxoplasmosis, rubella, etc.).
  • Parents who are carriers of genetic disorders, such as thalassemia, cystic fibrosis, etc.
  • Maternal age (after the age of 35).
  • At the pregnant woman’s request, due to excessive anxiety about the possible presence of chromosomal abnormalities.
What should I expect after amniocentesis?

During the first 24 hours, you may experience period-like cramps or even pain in the lower abdomen. This is normal, as is the occasional occurrence of light, spotting vaginal bleeding.

In many cases, taking a simple analgesic tablet that is safe during pregnancy, such as paracetamol (Depon), can help.

It is not normal to experience acute abdominal pain, have a fever, vaginal bleeding, or leakage of amniotic fluid (“your waters break”). In all these cases, you should seek immediate medical advice.

When will I receive the results?

The initial results for chromosomal abnormalities, such as Down syndrome, are usually available within two to three days (PCR). The fetal karyotype (culture) and information regarding other abnormalities / syndromes / diseases / infections are available within two weeks of the amniotic fluid sample being taken. As soon as we have the results, we will contact you immediately.

What are the risks of amniocentesis?

The risk of miscarriage, as described in the international literature, is in the order of 1/1000. A very small risk of maternal infection is described (1 in 1000), and for this reason it is recommended that the maternal temperature be recorded for the following two 24-hour periods. In the event of fever, clinical assessment and possible initiation of antibiotic treatment are recommended.

Ultrasound-guided invasive procedure

Polyhydramnios

Amnioreduction for polyhydramnios

  • DurationApproximately 10–15 minutes

This procedure reduces the volume of amniotic fluid in cases of polyhydramnios, with the aim of relieving the pregnant woman from severe discomfort and/or shortness of breath, as well as reducing the risk of premature rupture of the membranes and preterm birth.

The test in detail

The method applied is similar to amniocentesis. The entire procedure takes approximately 10–15 minutes. During this time, we can aspirate up to 1,500 ml of fluid, while a portion of the sample may be sent for further testing to a specialized cytogenetics laboratory.

Therapeutic amnioreduction for polyhydramnios is an invasive procedure and carries risks, the most common being miscarriage, at a rate of 1%. The risk is lower when the procedure is performed by an appropriately trained and certified physician.

NIPT

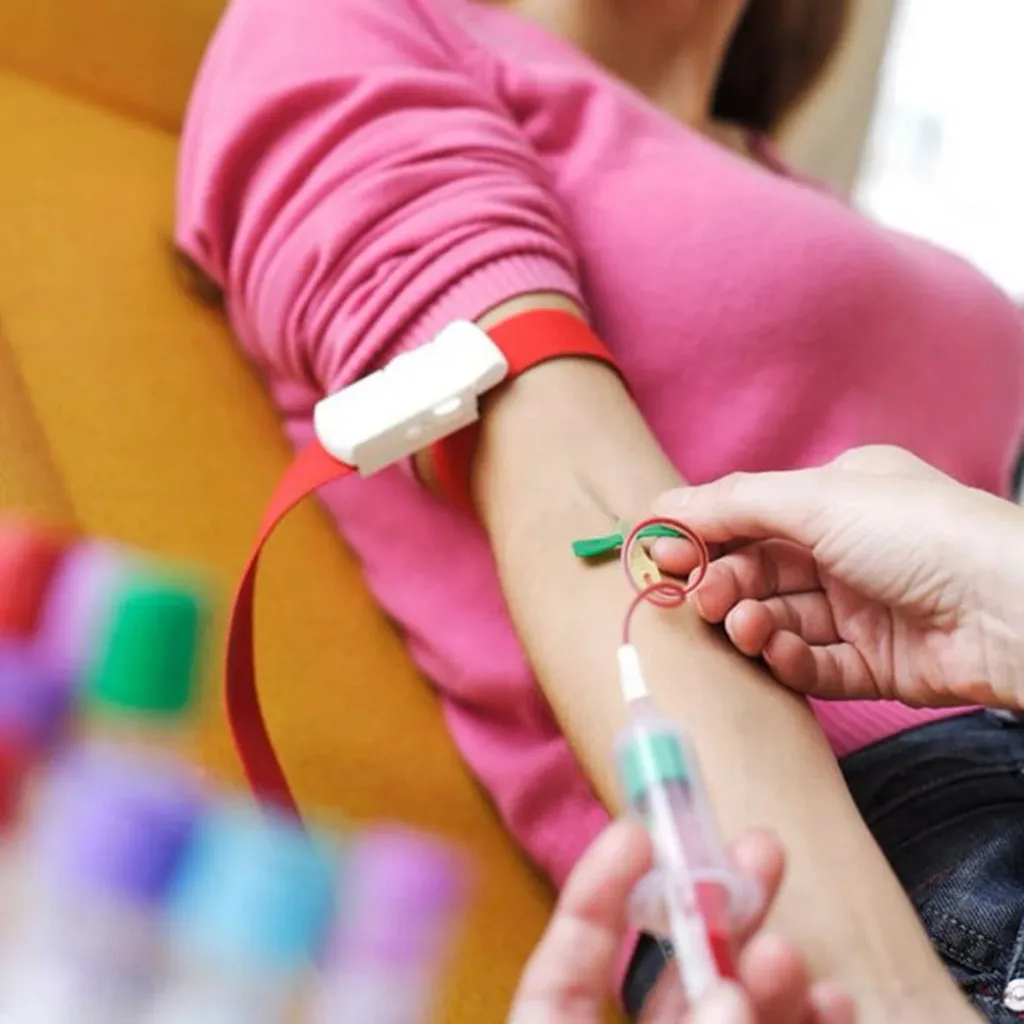
Blood sample being taken from the pregnant woman's arm

NIPT

Cell-free fetal DNA testing in maternal blood

  • When it is performedFrom the 10th week, ideally around the 11th
  • Results10–14 days

This is a method by which, in a blood sample from the 10th week of pregnancy, cell-free fetal DNA can be detected in the maternal circulation.

The test in detail
What is the usefulness of NIPT?

Based on current data and the limitations of the test, we recommend it mainly for women at “intermediate” risk, that is, in cases where the nuchal translucency scan indicated a risk of 1:250–1:1000 and provided that the nuchal translucency measurement is within normal limits. In these cases, we use NIPT because we want something more reliable than the nuchal translucency scan, but the findings are not sufficiently concerning to recommend invasive testing (amniocentesis or CVS). Conversely, if the nuchal translucency is abnormal (increased), NIPT is not the appropriate test for you, and amniocentesis or chorionic villus sampling is recommended.

The American College of Obstetricians and Gynecologists (ACOG) extends the recommendation for chromosomal screening to other cases considered “high risk” for chromosomal abnormalities, including women over the age of 35 or those with a relevant previous medical history.

Finally, the test is also offered to any pregnant woman who simply wishes to have it, without belonging to any of the above groups.

How is it performed?

It is a simple blood test taken from the woman’s arm, like any other blood test. At present, there are no laboratories in Greece that can test the sample, so the sample is packaged and sent to the USA.

When is it performed?

Ideally, the best time to perform the test is around 11 weeks. At 12 weeks, the detailed first-trimester ultrasound will follow, including measurement of nuchal translucency, and the results will be assessed together. In practice, however, it can be performed at any gestational age.

When can we expect the result?

The results are usually available within 10–14 days. There is approximately a 5% chance that no result will be obtained. This does not indicate a positive or negative result: it is a failed test, mainly due to low fetal DNA in the maternal blood. A repeat test will be offered.

How is the result expressed?

The result is expressed as a probability. It is a screening test and not a diagnostic test. A low-risk result means that the risk of a chromosomal abnormality is less than 1:10,000 and that, in more than 99% of cases, the fetus does not have the above chromosomal abnormalities. A high-risk result means that, in more than 99% of cases, the fetus will have Trisomy 21, 18, or 13, and in this case an invasive test will be offered to confirm the result.

What is the difference from amniocentesis?

In Medicine, there are diagnostic tests, which will confirm or rule out a pathological condition with 100% certainty, and screening tests, which assess the probability or, in other words, the risk of the presence of a pathological condition. Screening tests may be more or less accurate in their assessment. For example, a very good screening test is the Pap test, which essentially assesses the probability of cervical cancer being present. This is followed by the diagnostic test, namely a cervical biopsy and other paraclinical examinations.

What is the role of NIPT?

To be determined!

It is certainly a better screening test than the measurement of nuchal translucency and PAPP-A, as the sensitivity of the method approaches 99% (versus 96%). In addition, the screening covers trisomies 18 and 13 (as does nuchal translucency), as well as 7 additional genetic syndromes at present, depending on the company. However, it is not a diagnostic test. Nor, of course, is the measurement of nuchal translucency.

In other words, if NIPT indicates a reduced risk for Down syndrome, the likelihood of its presence is minimal; and if the risk is increased, confirmation with a diagnostic test is required, namely amniocentesis or CVS (chorionic villus sampling – placental biopsy).

NIPT does not replace amniocentesis.Amniocentesis cannot be performed indiscriminately and with lax criteria, because it is associated with a small but real risk of miscarriage.

BOOK AN APPOINTMENT

Book an appointment.

Dr. Alexandros Traianos, Diploma holder in Fetal Medicine, provides all invasive and non-invasive methods of prenatal screening.